This website is intended for UK healthcare professionals.
The Adverse Event Reporting and a link to the Prescribing Information can be found at the bottom of the page.

Elvanse could open up a world of new opportunities:

Elvanse® is indicated for ADHD as part of a comprehensive treatment program for children (6 years and over) when response to methylphenidate is considered clinically inadequate and in adults with pre-existing childhood ADHD symptoms.1

Treatment must be supervised by a specialist in behavioural disorders appropriate to the patient’s age1

Elvanse® is not indicated for all ADHD patients and the decision to use the medicinal product must consider the patient profile, including symptom severity, chronicity, potential for abuse, misuse or diversion, and clinical response to previous pharmacotherapies for ADHD.1

Elvanse logo

NICE Guidelines

NICE recommends LDX for children and young people who have had a 6-week trial of MPH at an adequate dose and not derived enough benefit in terms of reduced ADHD symptoms and associated impairment1

NICE recommends that…

Icon

… when prescribing stimulants for ADHD, think about
modified-release once-daily preparations for the following reasons:1

Icon
-

convenience

-

improving adherence

-

their pharmacokinetic profiles

-

reducing problems of storing and administering controlled drugs at school

-

the risk of stimulant misuse and diversion associated with immediate-release preparations

-

reducing stigma (because there is no need to take medication at school or in the workplace)

In adults (18+) lisdexamfetamine or MPH* are recommended as first-line treatment options for adults with ADHD.2
*Not all methylphenidate preparations are licensed for use in adults - see individual product SmPCs for details. MPH=methylphenidate.

Elvanse helps children and young people with
ADHD meet the growing demands of their lives

LDX=lisdexamfetamine dimesylate; MPH=methylphenidate.

What prodrug technology could mean for patients
with ADHD

*The decision to use Elvanse must take into consideration the profile of the patient, including the potential for abuse, misuse or diversion.
LDX=lisdexamfetamine dimesylate; MPH=methylphenidate.

Elvanse provides 13 hours of sustained and consistent core
symptoms control in children2,7

When taken at 7:00 am, Elvanse provided
symptom control up to 8:00 pm (13 hours)1

Primary outcome:

Elvanse provided significant improvement on the SKAMP-D subscale at 1.5 hours, compared with placebo (p<0.005)

Secondary outcome:

Elvanse demonstrated significant improvements in SKAMP-A and SKAMP-D subscales at all time points up to and including 13 hours postdose

Adapted from Wigal SB et al. Child Adolesc Psychiatry Ment Health. 2009; 3(1): 17
In a Phase 3b, randomised, double-blind, multicentre, placebo-controlled, dose-optimised, crossover study, children aged
6-12 were administered daily Elvanse for one week followed by placebo for one week, or vice versa (n=117). Primary endpoint
data includes LS mean change on SKAMP-D subscale at each timepoint and mean score throughout the day1
*p<0.005, **p<0.001 vs. placebo.
LS=least-squares; SKAMP=Swanson, Kotkin, Agler, M-Flynn and Pelham scale, D=deportment, A=attention.

A network meta-analysis rated amfetamines, including
lisdexamfetamine, as the most efficacious compounds
in child and adolescent patients1

-

In adults, amfetamines were rated as the preferred first-choice medications for the short-term treatment of adult ADHD1

Adapted from Cortese S et al. The Lancet Psychiatry. 2018: 5(9): 727-38.
A meta-analysis of 133 double-blind randomised controlled trials (including 81 in children and adolescents, 51 in adults,
and one in both), aimed at comparing the efficacy of ADHD medications. Plots include all trials for efficacy and tolerability
and are compared with placebo as reference. In total, 14,346 children and adolescents and 10,296 adults were included.1
Please note these trials were not head-to-head comparator trials.
CI=confidence interval; SMD=standardised mean difference.

Long-term data suggest an adaptation to
selected TEAEs of special interest* over time1

Adverse reactions observed with Elvanse mainly reflect side effects commonly associated with stimulant uses.

Very common (≥ 1/10) and common (≥ 1/100 to < 1/10) AEs in children (6-1 2 years)were: decreased appetite, insomnia†, tic, affect liability, aggression, headache, dizziness, somnolence, tachycardia, dry mouth, diarrhoea, constipation, upper abdominal pain, nausea, vomiting, rash,irritability, fatigue, pyrexia, weight decreased.

Very common (≥ 1/10) and common (≥ 1/100 to < 1/10) AEs in adolescents (13-17 years) were:decreased appetite, insomnia†, anxiety, depression, headache, dizziness, restlessness, tremor, somnolence, tachycardia, palpitation, dysponea, dry mouth, diarrhoea, upper abdominal pain, nausea, vomiting, irritability, fatigue, feeling jittery, pyrexia, weight decreased.

Very common (≥ 1/10) and common (≥ 1/100 to < 1/10) AEs in adults (18 years and over) were: decreased appetite, insomnia†, agitation, anxiety, libido decreased, affect lability, psychomotor hyperactivity, bruxism, headache, dizziness, restlessness, tremor, tachycardia, palpitation, dysponea, dry mouth, diarrhoea, constipation, upper abdominal pain, nausea, hyperhidrosis, erectile dysfunction, chest pain, irritability, fatigue, feeling jittery, blood pressure increased, weight decreased.

Adapted from Coghill DR et al. CNS Drugs. 2017; 31: 625–38.
A Phase 4, European, multicentre, open-label, 2-year study aimed to analyse the long-term tolerability
and safety of Elvanse in children aged 6-17 (n=314).1
*Selected TEAEs of special interest (decreased appetite, insomnia†, weight decreased and headache)
were pre-specified by the study sponsor based on their reported association with stimulant treatment.
†Including preferred terms insomnia, initial insomnia, middle insomnia and terminal insomnia.
TEAE=treatment-emergent adverse event.

CYP patients on second-line Elvanse stayed on treatment
longer than those on MPH1

Adapted from Giacobini M, et al. J Atten Disord. 2023; 27(12): 1309–21.
In an observational retrospective study evaluating treatment patterns for ADHD in Sweden, which included cross-sectional
and longitudinal analyses of patients with ADHD from the Swedish National Patient Register and Prescribed Drug Register
(2018 to 2021), Elvanse demonstrated a longer treatment duration compared to methylphenidate (n=243,790).1
*This study may have limited generalisability to the UK.
CYP=children and young people; MPH=methylphenidate.

Elvanse significantly improved key quality-of-life measures
including achievement and risk avoidance1

-

Patients treated with Elvanse reported significantly higher achievement scores and improved risk avoidance compared with placebo

(achievement: 40.3 vs 29.3, p<0.001; risk avoidance: 49.8 vs 41.6)1

Adapted from Banaschewski T et al. CNS Drugs. 2013; 27(10):: 829-40.
*Seven-week, randomized, double-blind, placebo-controlled, phase III study in children and adolescents aged 6–17 with a baseline
ADHD-RS-IV total score ≥ 28. Patients were randomized (1:1:1) to dose-
optimized Elvanse (30, 50, or 70 mg/day; n=104), OROSMethylphenidate as a reference treatment (18, 36, or 54 mg/day; n=107), or placebo (n=106). The primary efficacy outcome was the
improvement on the ADHD-RS-IV scale. Achievement domain was pre-specified as a health-related quality of life (HRQL) outcome.
†Elvanse did not achieve statistical significance in the Comfort domain or the Physical Activity and Satisfaction
with Self subdomains.1
CI=confidence interval; SMD=standardised mean difference.

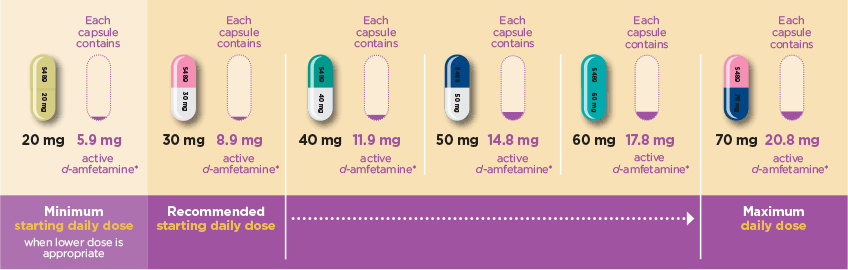
Simple, flexible dosing and titration1

Elvanse has a range of six once-daily dose strengths for flexible, precision dosing1

Elvanse recommended dosing
-

The dose may be increased by 10 or 20 mg increments, at approximately weekly intervals

-

Elvanse should be administered at the lowest effective dosage

-

One license for children aged 6 years and over, and adults

*For illustrative purposes only. Based on % of total weight and a 100% full capsule.
†In patients with severe renal insufficiency the maximum daily dose should not exceed 50 mg.1

References

  1. NICE. Attention deficit hyperactivity disorder: diagnosis and management. NG87.
    Available at nice.org.uk/guidance/NG87 (accessed March 2023).
  2. Elvanse. Summary of Product Characteristics.
  3. Wigal SB et al. Child Adolesc Psychiatry Ment Health 2009;3(1):17.
  4. Banaschewski T et al. CNS Drugs; 28(12): 1191-203.
  5. Coghill DR et al. CNS Drugs. 2017; 31(7): 625-38.
  6. Soutullo C et al. CNS Drugs. 2013;27(9):743-5.